


A general-purpose chatbot is not a medical care relationship. It can explain wording or suggest blank headings, but it has not examined you, established a complete history or arranged accountable follow-up. A confident answer cannot decide a diagnosis, medicine change or whether it is safe to wait.
If a medical emergency may be happening, contact local emergency services now and follow their instructions. Do not describe the situation to a chatbot first. If you need urgent help but do not know the right service, use an official clinical triage route. NHS 111 is an England-specific example; it is distinct from emergency response. In the EU, 112 is the emergency number.
Choose the next source, not a more persuasive prompt
Keep real health details out of a general-purpose chatbot, including when asking about a general term. Use public educational text or blank structures; take your personal circumstances to the appropriate care service.
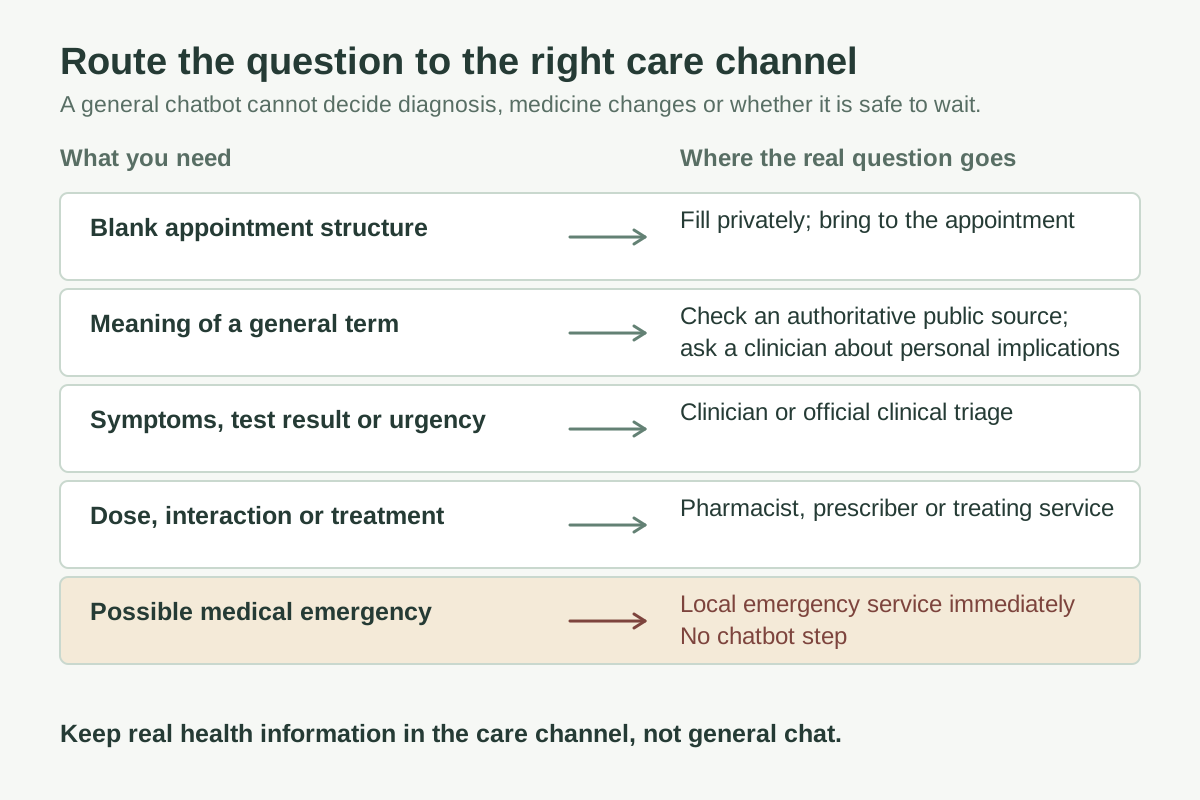
| What you need | Appropriate role for AI, if any | Where the real question goes |
|---|---|---|
| A blank appointment structure | Optional generic headings, with no real health data | Fill it privately and bring it to the appointment |
| The meaning of a general health term | A tentative explanation checked against an authoritative source | Ask a clinician or pharmacist about personal implications |
| Interpretation of your symptoms or test result | Do not make the decision in general chat | Clinician or official clinical triage service |
| A dose, interaction or treatment decision | Do not act on generated advice | Appropriate pharmacist, prescriber or treating service |
| Possible emergency | No chatbot step | Local emergency service immediately |
The medical boundary card keeps these routes together. A disclaimer in an answer does not make the rest of it reliable.
Why the boundary matters
WHO’s guidance on large multimodal models identifies false, inaccurate, biased and incomplete health statements as potential sources of harm. It also warns about automation bias, where people overlook errors or delegate difficult decisions inappropriately.
A model may have access to tools or uploaded records. That does not establish that the records are complete, the tool is validated for your situation or the service has taken responsibility for your care. A provider-approved clinical system has a different scope and data arrangement from an ordinary consumer chat; follow the care provider’s instructions for that exact system.
A source-reading example
For general health literacy, start from a public source. The NHS appointment guide recommends preparing important questions and asking what happens next. A generic prompt could ask:
Turn the idea of asking about follow-up into three blank questions. Do not ask for symptoms, records or medicines, and do not supply medical answers.
AI-generated teaching output, checked for scope:
What should happen next? When should it happen? Who should I contact if the expected follow-up does not arrive?
The questions prepare a conversation. They neither assess urgency nor decide care. You can write them yourself without using AI.
Keep real health information in the care channel
Do not paste real symptoms, dates, lab values, medication lists or medical documents into a general-purpose chatbot. Removing a name does not make a distinctive health history anonymous. Use paper, your private records or a channel explicitly approved by your care provider for the exact data and purpose.
OpenAI’s data controls illustrate that opting out of training does not remove chat history; Temporary Chat has its own retention and sharing boundaries. Neither supplies clinical approval.
For a scheduled visit, use the manual appointment brief. Bring current medicine information; the FDA medication-list guidance explains why prescriptions, non-prescription products, vitamins and supplements belong in that record. If records conflict, ask the pharmacist or care team to reconcile them. Do not ask a model to choose which instruction is current.
When an educational question turns into “What does this mean for me?”, take that question to the appropriate care service. If timing is uncertain, use clinical triage rather than deciding on your own that it can wait.


